
Cartilage, Step on the Gas: New Treatments for Rare Growth Disorders
09. 11. 2026
People with achondroplasia are documented throughout history – from ancient Egypt to the courts of European kings. Only today has science reached a level where it can successfully unravel the complex causes of growth disorders and find treatment options. One researcher who has long focused on this topic is cell biologist Pavel Krejčí from the Institute of Animal Physiology and Genetics of the Czech Academy of Sciences, whose work we featured in A / Magazine, the annual English-language magazine of the Czech Academy of Sciences.
Seneb owned thousands of head of cattle, twenty palaces, and held numerous religious titles. A high-ranking official in ancient Egypt in the third millennium BCE, he had a beautiful wife and three healthy children. Yet he faced challenges. What set him apart from others was his unusual stature. His torso was average-sized, but his head was somewhat larger and his arms and legs were markedly short. Seneb is the earliest known historical figure with the genetic growth disorder now known as achondroplasia.
Today, an estimated 350,000 people worldwide live with this rare diagnosis; in the Czech Republic, there are fewer than one hundred. This genetic disorder arises before birth, and although the condition can be inherited, up to 90 percent of children with achondroplasia are born to parents who don’t have the disorder, as a result of a new mutation. According to some theories, the risk of errors in intricate DNA sequences increases with the father’s age, though this isn’t entirely clear. In fact, many questions about achondroplasia remain unanswered.
California, the Centre of Research
Since the early 1990s, one thing has been certain: achondroplasia is caused by a mutation in a gene abbreviated as FGFR3. “An enormous amount of research was done in the first six years after the discovery of the FGFR3 mutation in 1994. I entered the field around the turn of the millennium and, to be honest, I thought everything had already been explored. The opposite turned out to be true,” says Pavel Krejčí from the Institute of Animal Physiology and Genetics of the CAS.
“The reality is that we understand perhaps ten percent of the achondroplasia mechanism. The rest remains largely unknown,” adds Krejčí, who in 2001 left his alma mater, Masaryk University, to gain experience at the Cedars-Sinai Medical Center in Los Angeles. At the time, this institution was at the forefront of research into growth disorders, including achondroplasia, and it’s no coincidence that the first breakthrough discoveries were made there thirty years ago.
Researchers there had access to samples from patients with growth disorders from across the USA. Thanks to a carefully maintained and continuously updated registry, they’ve identified many different types of skeletal conditions in humans.
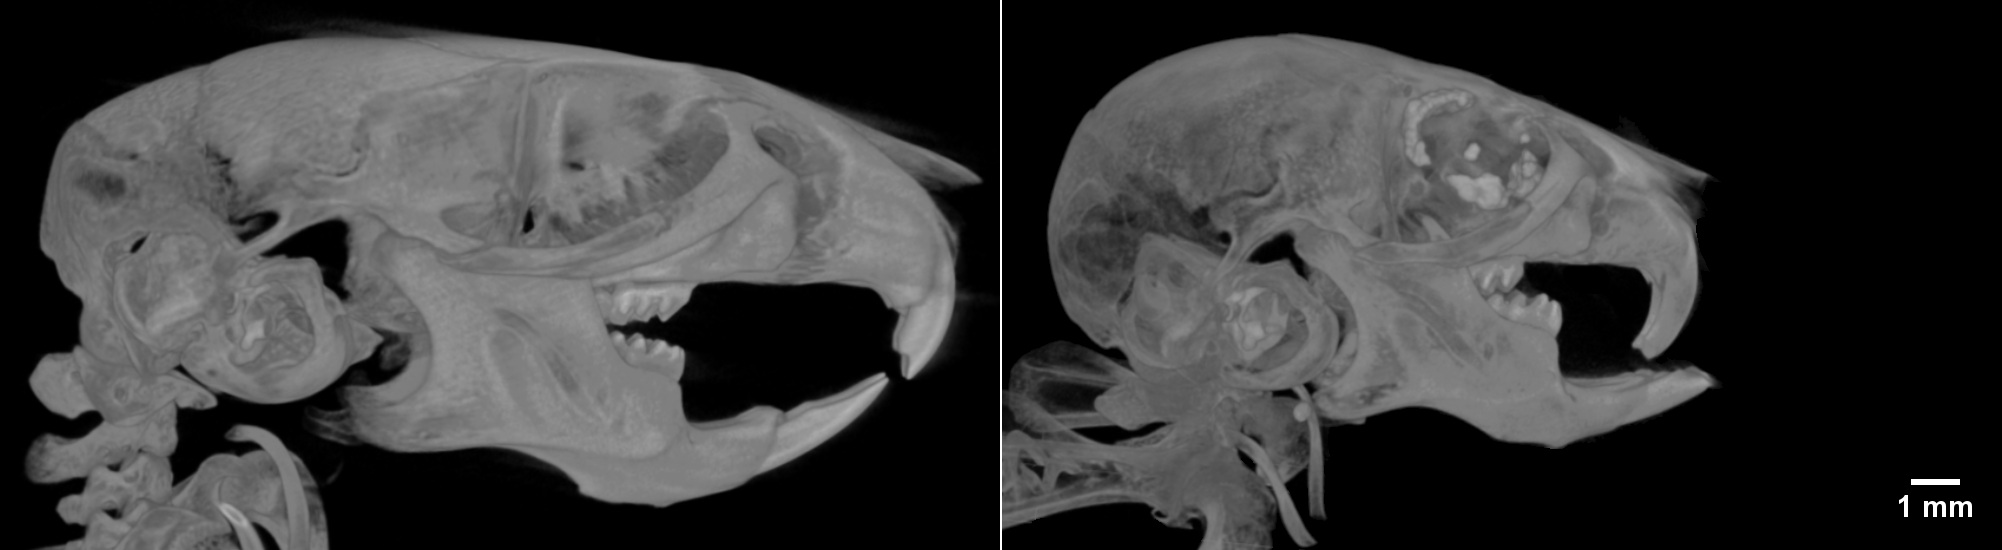
Micro-computed tomography (mCT) images of normal (left) and achondroplastic (right) mouse skulls at postnatal day 35.
A Natural Laboratory
In the case of achondroplasia, one of the main suspects – and indeed the culprit – is the mutated FGFR3 gene. This gene plays a crucial role in bone development but also influences processes in other parts of the body, so its disruption can cause serious issues. It’s one of the more frequently mutated human genes, and some of its variants are associated with cancer, including liver cancer and bladder cancer.
Many research teams around the world study the functions and defects of FGFR3, but most focus on cancer, where FGFR3 behaves in exactly the opposite way to what we see in achondroplasia. While cancer involves accelerated and uncontrolled cell proliferation, achondroplasia is characterised by the inhibition of cell growth.
A mutation in the gene leads to dysfunction of the protein of the same name, FGFR3, which stands for fibroblast growth factor receptor 3. A receptor is a molecule on the surface of a cell that enables communication. This particular receptor is located on the surface of a chondrocyte – a cell responsible for the growth and formation of cartilage (connective tissue).
When FGFR3 malfunctions due to a genetic mutation, the transmission of information falters, and development in the body goes awry. “We can view growth disorders – and achondroplasia in particular – as an ideal lab for studying cellular communication. Pathologies actually teach us how the organism is supposed to function properly,” Krejčí says.

In achondroplasia research, scientists work with mouse models. The image shows colorized skulls – purple indicates bone, blue indicates cartilage. (CC)
To better understand this, we can picture FGFR3 as a modulator of bone growth that determines how quickly or slowly cartilage cells can divide and mature. Under normal conditions, it acts as a gentle brake regulating the entire process. It tells the body: “Wait, it’s not yet time to lengthen the bones,” or “Proceed, but gradually and steadily.” However, if the guardian becomes overactive due to a genetic mutation, the brake gets stuck and cannot be released. The growth of long bones slows down or ceases altogether. This is exactly what happens in patients with achondroplasia. Their braking system is excessively active, and the bones of the arms and legs stop lengthening around the age of four.
Less Brake, More Gas
If scientists were able to determine how to effectively influence the inordinate activity of this braking system, they could solve the problem of halted bone growth. It sounds simple, but the entire communication system between the receptor and the cell is far more complex. Information is transmitted through intercellular signals known as ligands – in this case, growth factors from the FGF family. If we visualize the receptor (such as FGFR3) as a lock, then the ligand (FGF) is the key that opens it.
Pavel Krejčí’s team, together with colleagues from Johns Hopkins University in Baltimore, is currently trying to determine how a single receptor can distinguish among four different ligands. It’s similar to an ear listening to four voices at once and the brain understanding what each of them is saying at any given moment.
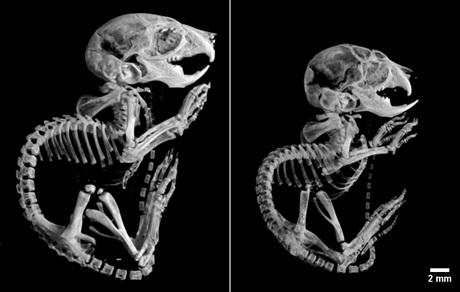
Whole-body mCT scans of normal (left) and achondroplastic (right) mice.
Some communication pathways, however, are already known, and stimulating the right signalling channels underlies Voxzogo, the first approved drug for achondroplasia, whose development Krejčí was involved in at the beginning. The drug delivers an artificially created signalling molecule into the body that reduces the inhibitory activity of FGFR3 and thus promotes bone elongation. Administered as a daily subcutaneous injection, Voxzogo is intended for children with confirmed achondroplasia whose growth is not yet complete.
Hope for the Future
The EU approved the drug in 2021, and it’s also used in the USA. The results are encouraging. According to available studies, children treated with Voxzogo grew 1.5 centimetres more per year than patients who received a placebo.
However, the drug is expensive, and its short-term effects are modest. As a result, insurance companies have been reluctant to cover it, and physicians can’t prescribe Voxzogo to everyone who might benefit from it.
So far, most of the patients using the drug are in the USA (about 40% of children with achondroplasia). In the Czech Republic, Voxzogo is currently used by several dozen patients, and Slovakia is just beginning to administer it. Meanwhile, experts from pharmaceutical companies and scientists – including Krejčí’s team – are working on a new generation of drugs that could work even better. Their aim is to find therapeutic approaches that would influence development at the earliest stages of life, maybe even prenatally. Although standard prenatal testing can’t detect the genetic mutation responsible for the growth disorder, an experienced gynaecologist can recognise it on ultrasound.
|
ACHONDROPLASIA IN NUMBERS 771 rare growth disorders are currently known; the most common one is achondroplasia. 130 centimetres is the average height of an adult man with achondroplasia. 90 percent of parents of children with achondroplasia are of normal height; the genetic mutations arise de novo in the father’s sperm. 350,000 is the estimated number of people with achondroplasia worldwide. 1 in 15,000–25,000 is the rate of children born with achondroplasia globally. 1 in 12 paediatricians in the Czech Republic has encountered a patient with achondroplasia. >100 patients are included in the clinical registry of individuals with achondroplasia in the Czech Republic and Slovakia. CZK 30 millionis the amount Pavel Krejčí can use for research over the next six years thanks to the Academic Award - Praemium Academiae he received from the CAS. |
“A specialist in growth disorders can detect it early in the second trimester. However, it must be acknowledged that a general gynaecologist won’t recognise achondroplasia until much later,” Krejčí adds. “Our estimate suggests that, in practice, one in twelve Czech paediatricians will encounter achondroplasia at some point in their career.”
Working Together in Synergy
A major advantage that helps Krejčí in researching rare growth disorders is the synergy between institutions. He has long been affiliated with the CAS as well as the Faculty of Medicine and the International Clinical Research Center of Masaryk University and St. Anne’s University Hospital in Brno. This provides him with both top-tier facilities and direct links to physicians and patients. At the Faculty of Medicine, he established the Registry of Achondroplasia (ReACH), which currently contains records of several dozen paediatric patients from the Czech Republic and Slovakia.
The registry helps researchers better understand the medical aspects of achondroplasia. For patients and their families, it offers an opportunity to provide feedback to experts. The registry has also yielded a somewhat surprising finding. Most fathers of children with achondroplasia were of typical age at the time of conception – at least among Czech parents, the assumption that advanced paternal age is a risk factor for mutations in the growth gene hasn’t been confirmed.
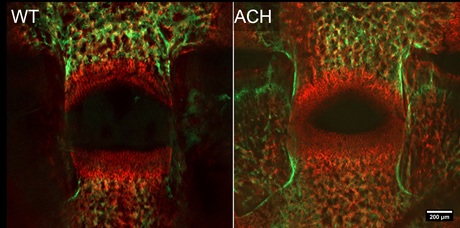
Calcein (green, embryonic day 17.5) and alizarin red (red, postnatal day 1) staining reveals premature fusion of the bones in the skull base of mice with achondroplasia (ACH), indicating that the fusion process initiates during embryonic development (WT, healthy animal).
However, it’s known that the FGFR3 gene somehow impacts the development and function of sperm – one of many research aspects pursued by Krejčí’s team. The FGF signalling system evolved over approximately 700 million years, from jellyfish to humans, and is highly complex. In addition to bone development, it regulates most other cellular processes involved in human growth and development. From this perspective, studying achondroplasia offers scientists an exceptional opportunity to understand the mechanisms of life at the cellular level.
Achondroplasia in History Books
Conducting large-scale research wouldn’t be possible without adequate funding – for Krejčí’s group, this has been provided since 2024 by the Academic Award - Praemium Academiae. “We’re developing medicine for future generations. The development and testing of Voxzogo took fifteen years. A new class of treatments will be approved within a matter of years,” Krejčí says. The drugs his team is working on now – which may one day fully resolve the skeletal symptoms of achondroplasia – are expected to become available within the next decade.
“It’s a long-distance run, and in many ways, research is comparable to elite sports. You train, fight, and push yourself to the limit, you try to stay at the top and compensate for waning strength. The Award has given me the power to run another lap.”
As the highest grant awarded by the CAS, the Praemium Academiae amounts to CZK 30 million over six years. Its advantage lies in its flexibility and the freedom it offers by reducing the administrative burden. Krejčí doesn’t intend to spend the funds on upgrading lab equipment, not needing new instruments. Instead, he sees real value in people – their enthusiasm, intellect, and abilities – and plans to invest primarily in his team.
Krejčí knows many of the families of children with achondroplasia personally, both in the Czech Republic and Slovakia, and deeply wishes to improve their lives. At the same time, he is aware of the limitations of the current therapy – it hasn’t been in use for very long, and its long-term benefits are yet to manifest.
“The ultimate goal is to relegate achondroplasia to the history books, but we aren’t there yet. My main ambition is to do everyday, ordinary scientific work well. I still find that immensely enjoyable,” the cell biologist says. “I’m like a car mechanic who looks forward to every new vehicle,” he adds. The automotive analogy is no coincidence. In addition to being an avid motorcyclist, Krejčí has always had a strong interest in technology – he has long seen parallels between the world of engines and cellular communication. Cells are intricate mechanical systems, and there is nothing more satisfying than seeing them work like well-oiled machines – something Krejčí’s work helps make possible.
|
Pavel Krejčí Jako buněčný biolog se dlouhodobě věnuje výzkumu mezibuněčné komunikace prostřednictvím receptorů pro růstové faktory. Zaměřuje se zejména na roli FGF receptorů, jež zásadně ovlivňují vývoj a růst chrupavek a kostí, a na to, jak jejich genetické poruchy vedou k závažným onemocněním lidské kostry. Téměř 20 let působil v zahraničí, nejdéle v americkém Cedars-Sinai Medical Center a na Kalifornské univerzitě v Los Angeles. V USA se podílel na vývoji léčiv na achondroplazii, genetickou poruchu způsobenou mutacemi v receptoru FGFR3, jež vede k nízkému vzrůstu. Po návratu do Česka založil klinický registr pacientů s touto vzácnou nemocí. V letech 2019 a 2023 získal ocenění za zdravotnický výzkum a vývoj od ministra zdravotnictví. V roce 2024 mu Akademie věd ČR udělila Akademickou prémii. As a cell biologist, Pavel Krejčí has long focused on research into cell communication mediated by growth factor receptors. He studies the role of FGF receptors, which are crucial for bone growth, and how their genetic defects lead to severe disorders of the human skeleton. Krejčí spent nearly twenty years working abroad, most notably at the Cedars-Sinai Medical Center and the University of California, Los Angeles. In the USA, he contributed to the development of treatments for achondroplasia, a genetic disorder caused by mutations in the FGF receptor 3 that leads to short stature. After returning to the Czech Republic, he established a clinical registry of patients with this rare disorder. In 2019 and 2023, he received awards for medical research and development from the Czech Minister of Health. In 2024, he was awarded the Praemium Academiae of the CAS. |
 (CC)
The article was first published in A / Magazine 2026.

Written and prepared by: Leona Matušková, External Relations Division, CAO of the CAS
Translated by: Tereza Novická and Aneta Ryntová, External Relations Division, CAO of the CAS
Photo: Pavlína Černoch Jáchimová, František Špoutil, Lucie Krátká, Gustavo Rico-Llanos
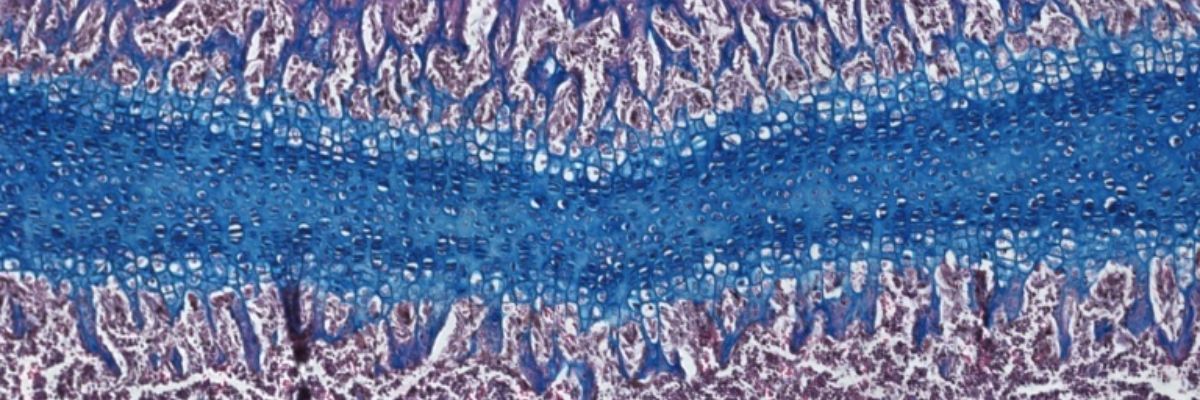
Cover photo: Histological section through growing cartilage in the skull base. Blue, cartilage; Red, bone
 The text and photos labelled CC are released for use under the Creative Commons license.
Read also
- Czech Academy of Sciences to Support Groundbreaking Research by Nine Scientists
- Water Is Not Enough for Settlement. Stone Was Equally Important
- A / Magazine: Toxins, Languages, and Lightning on Jupiter
- ERC-funded CLOSER Project Highlights the Middle East and North Africa Region
- Bernard Bolzano: An Inconvenient Genius Ahead of His Time
- Our Health in the Hands of AI: How to Regulate It and What to Watch Out For?
- CAS Condemns Attack on National Academy of Sciences of Ukraine
- New CAS Program Already Has First ERC Grant Winners to Its Credit
- Three researchers from the Czech Academy receive prestigious ERC grants
- Ombudswoman of the CAS Dana Plavcová: I'm glad when things change for the better
The Czech Academy of Sciences (the CAS)
The mission of the CAS
The primary mission of the CAS is to conduct research in a broad spectrum of natural, technical and social sciences as well as humanities. This research aims to advance progress of scientific knowledge at the international level, considering, however, the specific needs of the Czech society and the national culture.
President of the CAS
Prof. Radomír Pánek started his first term of office in March 2025. He is a prominent Czech scientist specializing in plasma physics and nuclear fusion.